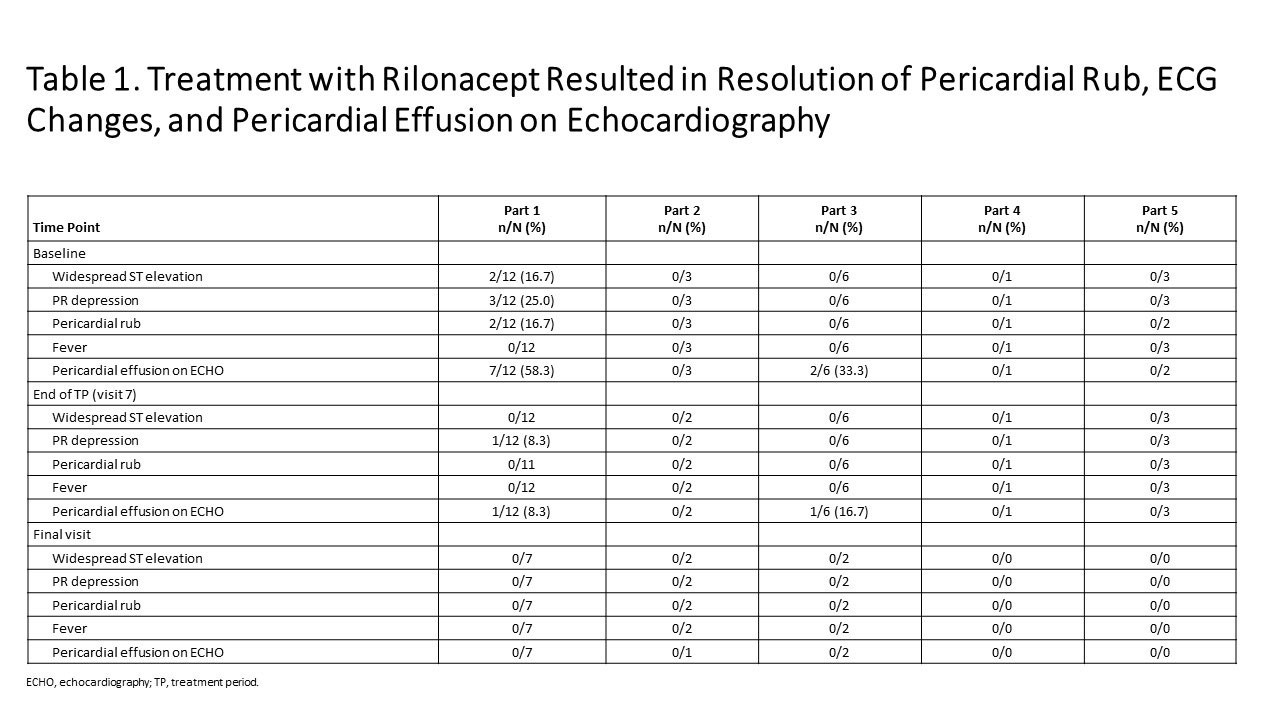
Patients who had a clinical response (i.e., met prespecified response criteria) were randomly assigned in a 1:1 ratio to receive continued rilonacept monotherapy or placebo, administered subcutaneously once weekly. The primary efficacy end point, assessed with a Cox proportional-hazards model, was the time to the first pericarditis recurrence.
- In the optional 18-week treatment extension period (EP), during which rilonacept weekly injections continued, investigators were given the option to wean their patients from concomitant medications as follows: for NSAIDs and colchicine to taper within 15 days of EP entry, and for CS to taper by 5 mg prednisone or equivalent each week in adults so as to withdraw within 6 weeks of EP entry. For active pericarditis patients (parts 1, 2 and 4), the primary efficacy endpoints were patient-reported pericarditis pain using an 11-point pain numeric rating scale (NRS), validated across multiple conditions with acute and chronic pain1012 and CRP at baseline and on-treatment.

Moving forward, it's essential to keep these visual contexts in mind when discussing The Efficacy Of Rilonacept.
Active treatment consisted of a loading dose of 320 mg rilonacept (KPL-914), administered via subcutaneous (SC) injection on day 0, followed by 160 mg SC weekly for five additional doses. An optional 18-week treatment-extension period was established, with the possibility of being cautiously weaned off concomitant anti-inflammatory medications. The primary efficacy outcome for patients with active disease was based on patient-reported pericarditis pain using an 11-point pain numerical rating scale (NRS) and CRP change.
- Recurrent pericarditis (RP) is ... RP, was effective in treating RP not only as a third-line agent (3L; after corticosteroids) but also as a second-line agent (2L; instead of corticosteroids) and reduced recurrence risk as monotherapy ...